Watch the 5-minute video

4:51 · English · Fictional examples. The video loads from YouTube only when you press play. Watch on YouTube
A useful stakeholder map should explain who is relevant to a medical objective, what evidence supports that assessment and what scientific work should happen next. A tier is a planning aid. It does not establish the value of an expert, validate a clinical opinion or replace the rationale for an individual engagement.
This article presents a practical workflow and shows how to apply it using the KOL Mapping and Tiering Essential workbook. Published recommendations support the underlying professional principles. The workbook’s scoring model is an illustrative, configurable approach rather than a validated classification.
Start with a medical question
Before listing names, define the scientific need. A team exploring variation in diagnosis may need clinical pathway expertise. A team assessing research feasibility may need investigators with relevant infrastructure. Write the objective in terms that a colleague can understand and review, then specify the geography, care setting and stakeholder roles that matter.
For this article, a key opinion leader (KOL) means an external expert with relevant scientific or clinical expertise and recognised contribution in a defined context. Stakeholder mapping is broader: it can include institutions, multidisciplinary teams and patient organisations whose perspectives are relevant to the question.
Keep selection grounded in science
The APPA, IFAPP, MAPS and MSLS position statement recommends identifying experts using relevant medical expertise, scientific contributions and professional roles. It advises against selecting experts because of prescribing potential or patient numbers. It also calls for a clear scientific purpose for subsequent engagements. [1]
For mapping, record why the person or organisation can contribute to the specific medical need. Keep commercial targets out of the assessment rationale.
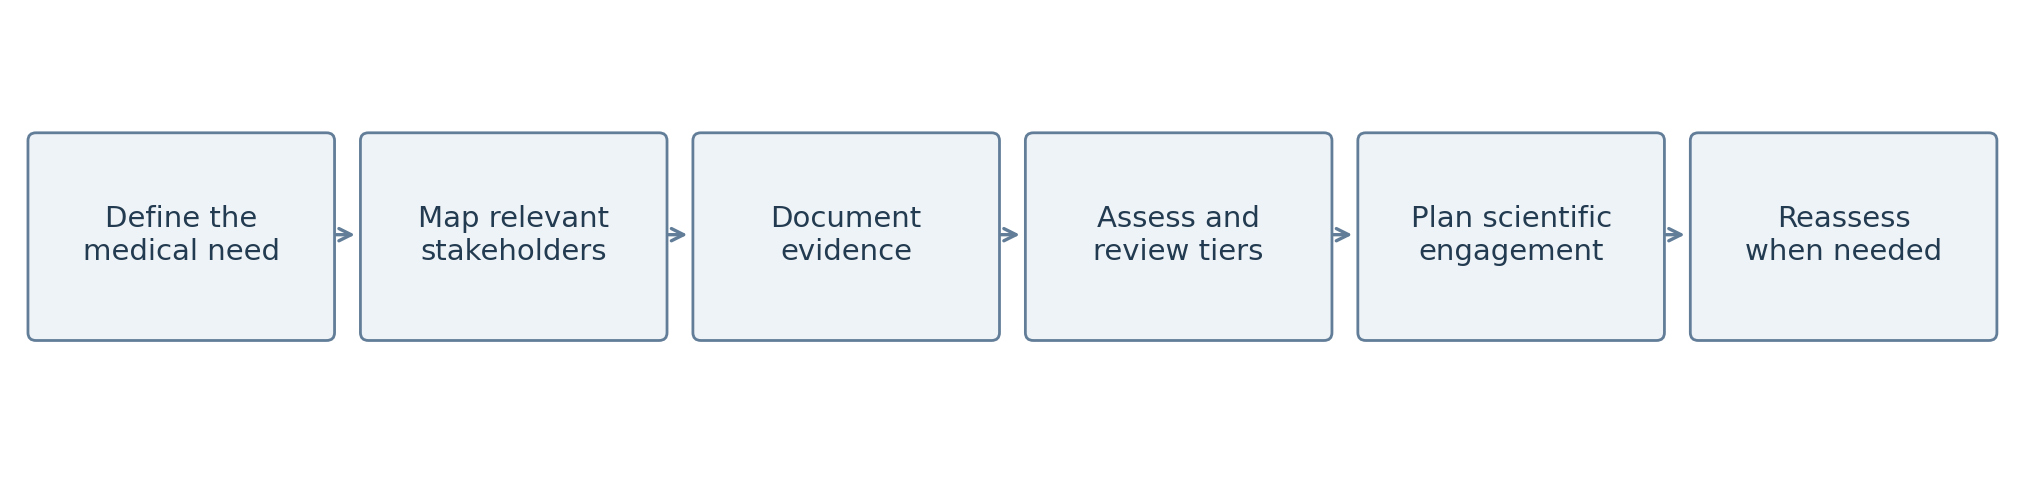
Figure 1. Proposed workflow developed for this article. The sequence is a practical recommendation, not a validated research model.
Assess contribution with documented evidence
Search across relevant sources such as published research, institutional biographies, professional society roles and documented scientific interactions. Confirm identity and current role. A source should support the particular judgement being made: an institutional title alone cannot establish research capability, and one meeting cannot establish broad peer recognition.
DORA recommends assessing research on its own merits rather than using a journal’s impact factor as a proxy for an individual’s contribution. Although DORA addresses research assessment rather than KOL tiering, the same caution is useful here: inspect the substance and relevance of the work. [2]
Seven dimensions in the Essential workbook
The following dimensions and weights are the workbook’s default design choices. They are not prescribed by the external references. Review their relevance before scoring, and use the workbook’s existing 1–5 descriptions consistently.
| Dimension | Default weight | Evidence to examine |
|---|---|---|
| Scientific Expertise | 20% | Relevant clinical or scientific experience and substantive contributions. |
| Scientific Influence | 15% | Documented scientific leadership, education and relevant peer recognition. |
| Strategic Relevance | 20% | A clear connection to the current medical objective or evidence question. |
| Evidence Generation | 15% | Relevant study experience, research infrastructure and feasibility. |
| Practice Impact | 10% | Documented guidance, education or care pathway contributions. |
| Engagement Potential | 10% | Relevant scientific interests and a feasible route for exchange. |
| Ecosystem Connectivity | 10% | Relevant multidisciplinary or institutional collaborations. |
Make the rationale reviewable
Replace labels such as “well known” with a source and an explanation of relevance. For example, “contributed to a recent multicentre study on the question under review” is more useful when the study and contribution are identifiable. Distinguish a verified fact from an assessor’s interpretation.
Assess contribution in the stakeholder’s context. A patient organisation and a clinical investigator serve different purposes; a direct numerical comparison may be misleading. If a criterion cannot be meaningfully supported, clarify the assessment approach before assigning a rating. An unknown value is not evidence of a low contribution.
Use scores as a structured judgement
In the Essential workbook, all seven dimension scores are integers from 1 to 5 and weights total 100%. The calculation is: weighted score = sum of dimension score multiplied by its decimal weight, divided by 5, then multiplied by 100. Under this formula, the possible range is 20 to 100, not 0 to 100.
The default Tier 1 minimum is 80; the Tier 2 minimum is 60. Scores below 60 fall into Tier 3. These thresholds are editable assumptions. Missing or invalid assessment fields can leave a record unscored. A score summarises the entered judgements; it does not make those judgements objective or scientifically validated.
A fictional worked example
| Demonstration stakeholder | Score | Tier | Engagement feasibility | Scientific Expertise | Scientific Influence | Strategic Relevance | Evidence Generation | Practice Impact | Engagement Potential | Ecosystem Connectivity |
|---|---|---|---|---|---|---|---|---|---|---|
| Dr Alex Morgan | 98 | Tier 1 | High | 5 | 5 | 5 | 5 | 5 | 4 | 5 |
| Dr Omar Reed | 89 | Tier 1 | Moderate | 5 | 4 | 5 | 5 | 4 | 3 | 4 |
| Dr Maya Chen | 68 | Tier 2 | High | 3 | 3 | 4 | 3 | 4 | 4 | 3 |
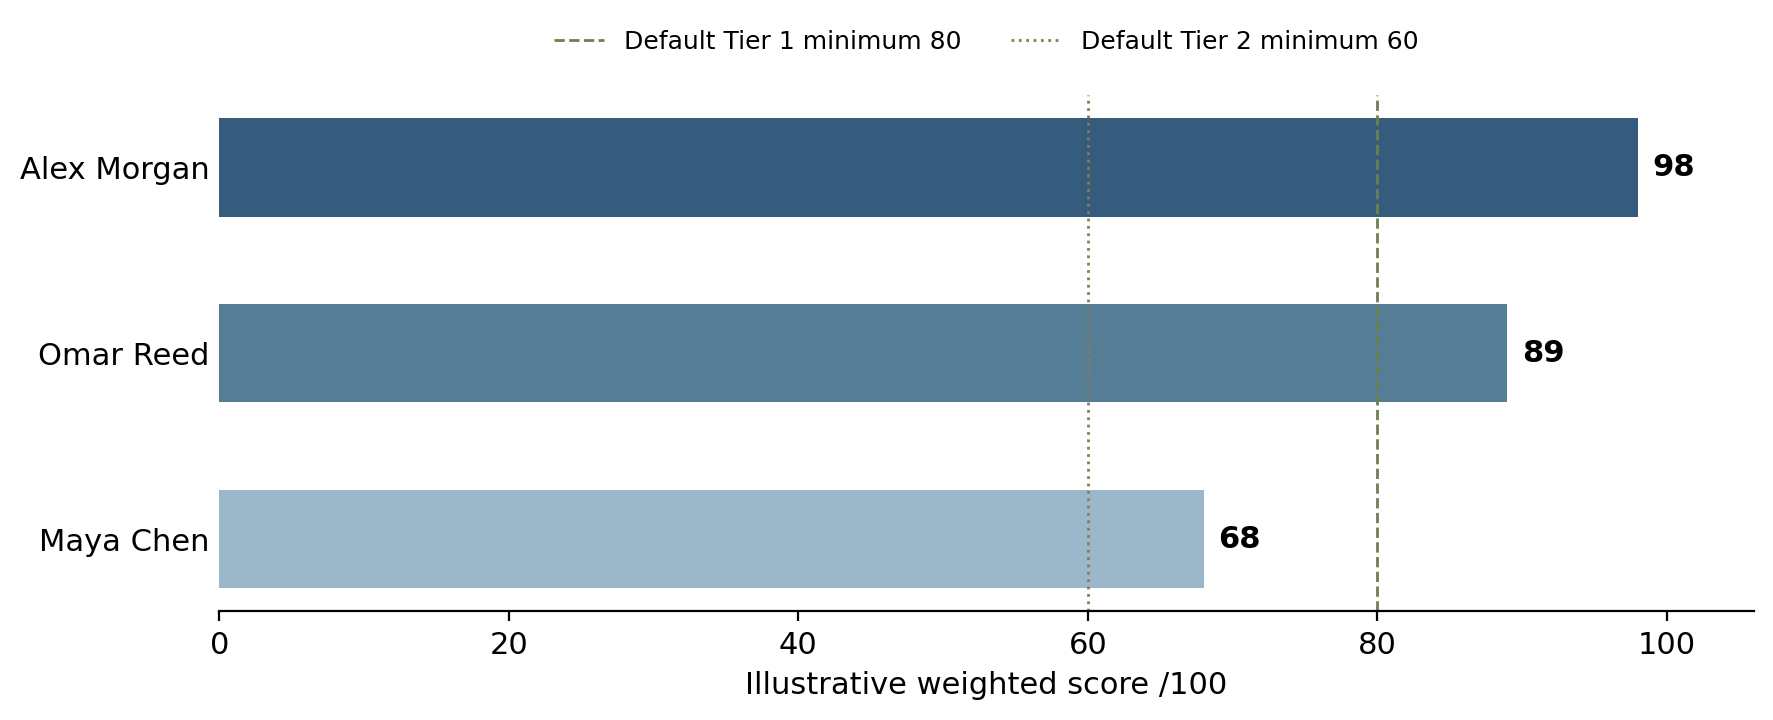
Figure 2. Fictional demonstration data from the Essential workbook. Dashed lines show default thresholds. These scores are not research findings or assessments of real people.
Alex Morgan’s example scores are 5, 5, 5, 5, 5, 4 and 5 in the dimension order shown on the previous page. The weighted sum is 4.9; dividing by 5 and multiplying by 100 gives 98. Their engagement rating of 4 is also displayed as High feasibility.
Omar Reed illustrates a useful distinction: a Tier 1 assessment can coexist with Moderate engagement feasibility. Engagement Potential contributes 10% to the total in this model and is also shown separately. Scientific relevance and practical access should both inform the next action.
Turn a tier into a scientific plan
A tier can help allocate attention, but a specific engagement still needs a purpose. For each stakeholder, record the question to explore, why their expertise fits, the appropriate format and who will follow up. Do not convert a tier automatically into a fixed visit frequency without considering the scientific need and available capacity.
Interpret the evidence within its limits
A 2019 Cochrane review of 24 studies found that interventions involving local opinion leaders probably improve adherence to evidence based practice. Effects varied, and improvement in patient outcomes remained uncertain. The review could not determine the comparative effectiveness of different approaches to identifying opinion leaders. [3]
This evidence concerns interventions supporting clinical practice. It does not validate an industry KOL scoring spreadsheet, establish the best tier thresholds or demonstrate that engaging a higher scoring stakeholder improves patient outcomes.
Review uncertainty and disagreement
Before acting on a ranking, ask another assessor to review a small sample independently. Compare the reasons for different ratings. Where a stakeholder sits close to a threshold, check whether a plausible change in a judgement would alter the tier. Record uncertainty rather than resolving it with an unsupported rating.
Avoid counting the same contribution several times simply because it fits several labels. A guideline role may inform expertise, influence and practice contribution, but the rationale should explain what each rating captures. Review whether the map omits relevant local clinicians, emerging researchers or disciplines with fewer publications.
Separate mapping from activity approval
An assessment does not approve a consultancy, research collaboration or advisory board appointment. As an example of an industry code, EFPIA’s 2026 Code requires contracted consultant selection criteria to relate to an identified legitimate need. Its contracted services provisions are distinct from routine stakeholder mapping. [4] Apply the rules and procedures relevant to the actual country, organisation and activity.
Keep the map current
Record an assessment date, review date and owner. Reassess when the medical objective, role, relevant evidence or engagement context changes. Keep a record of the reason for an update so a later reviewer can understand how the judgement developed.
Apply the workflow with the existing tool
The Essential workbook brings together stakeholder details, scientific interests, assessment rationale, seven ratings, a weighted score, tier and engagement feasibility. Review the Settings descriptions before using it. Record the supporting evidence and dates, then inspect the calculated result alongside the rationale. Its Dashboard summarises the full prepared table even when the mapping table is filtered.
Use the broader Stakeholder Strategy and Engagement System when the task also needs structured strategy links and follow through. For the initial mapping task, start with the Essential workbook and document the scientific reason for each next action.
References and practical review checklist
Before using a stakeholder assessment
• The medical objective and intended use of the map are clear.
• The stakeholder’s current identity, role and relevant contribution are supported by traceable evidence.
• The ratings follow the chosen descriptions, and uncertainty is recorded.
• The weights and thresholds are understood as model assumptions.
• The tier is considered alongside practical feasibility and the rationale for engagement.
• An owner and review date are recorded, and any proposed activity follows the applicable approval process.
References
1. Theron P, Britland M, Holder D, Ikeda Y, Rewers RF, Tiku A. Promoting Best Practices for Medical Science Liaisons Position Statement from the APPA, IFAPP, MAPS and MSLS. Therapeutic Innovation & Regulatory Science. 2021;55:1139–1144. doi:10.1007/s43441-021-00310-y.
2. DORA. San Francisco Declaration on Research Assessment. General recommendation and recommendations for research assessment.
3. Flodgren G, O’Brien MA, Parmelli E, Grimshaw JM. Local opinion leaders: effects on professional practice and healthcare outcomes. Cochrane Database of Systematic Reviews. 2019;6:CD000125. doi:10.1002/14651858.CD000125.pub5.
Read the review summary and abstract
4. European Federation of Pharmaceutical Industries and Associations. EFPIA Code of Practice. Final consolidated version 2026. Article 15, Section 15.02, page 23.
Online sources accessed 5 October 2026. Reference 1 is a professional position statement; reference 2 concerns research assessment; reference 3 is evidence about local opinion leader interventions; reference 4 is an industry code. None validates the workbook’s seven dimension model or default thresholds.
Companion resource and example provenance
KOL Mapping and Tiering Essential, version 1.0, 1 October 2026. The Settings, KOL Mapping and Quick Start tabs are the source of the formula, default settings and fictional examples in this article. The proposed workflow and practical review steps are professional recommendations developed for this article.
KOL Mapping and Tiering Essential
Explore the workbook, its instructions and its fictional examples before adapting it to your team.
View the matching workbook