Watch the 5-minute video

4:54 · English · Fictional examples. The video loads from YouTube only when you press play. Watch on YouTube
A stakeholder engagement plan should connect a medical question with relevant expertise, a purposeful scientific discussion and a documented next step. Mapping and tiering help identify whom to consider. Engagement planning explains why a discussion is needed, what the team hopes to learn and how the learning will be reviewed.
This article shows how to use the Stakeholder Strategy and Engagement System to maintain that connection. The workflow is a practical planning approach. It does not validate an expert’s opinion or establish that a recorded activity has produced a clinical benefit.
Define the purpose before scheduling the meeting
Begin with the medical objective and the question that remains unanswered. A request to “meet the top experts” provides little direction for preparation or follow up. A purpose such as “understand which outcome data are routinely captured in specialist centres” identifies the information needed and the expertise relevant to the discussion.
The APPA, IFAPP, MAPS and MSLS position statement describes scientific exchange, evidence generation support and insight gathering as MSL responsibilities. It recommends a clear scientific purpose for follow up meetings and independence from sales targets. [1]
Write an objective that can guide the discussion
| Vague planning statement | More useful scientific objective |
|---|---|
| Strengthen the relationship | Explore the expert’s current evidence questions and agree any relevant scientific follow up. |
| Discuss the new study | Review a defined study question, its limitations and relevance to the local care context. |
| Find a research advocate | Assess whether the investigator’s expertise and available data fit a specific evidence question. |
The desired result should describe learning or an appropriate medical deliverable. An evidence question refined, a feasibility issue documented or a scientific response completed can be reviewed. Agreement with the company’s interpretation should not be the purpose of the meeting.
Plan with the stakeholder
Confirm that the topic is relevant to the stakeholder, explain the purpose and use an appropriate format. Respect their availability and independent judgement. A well prepared scientific exchange can reveal disagreement or a lack of information; both may be useful findings when recorded accurately.
Connect the plan through the workbook
Use stable record IDs to keep the objective, stakeholder, discussion and follow up connected. The workbook separates the records because each answers a different question. A stakeholder may contribute to more than one objective or evidence gap, and each relevant combination needs its own link.
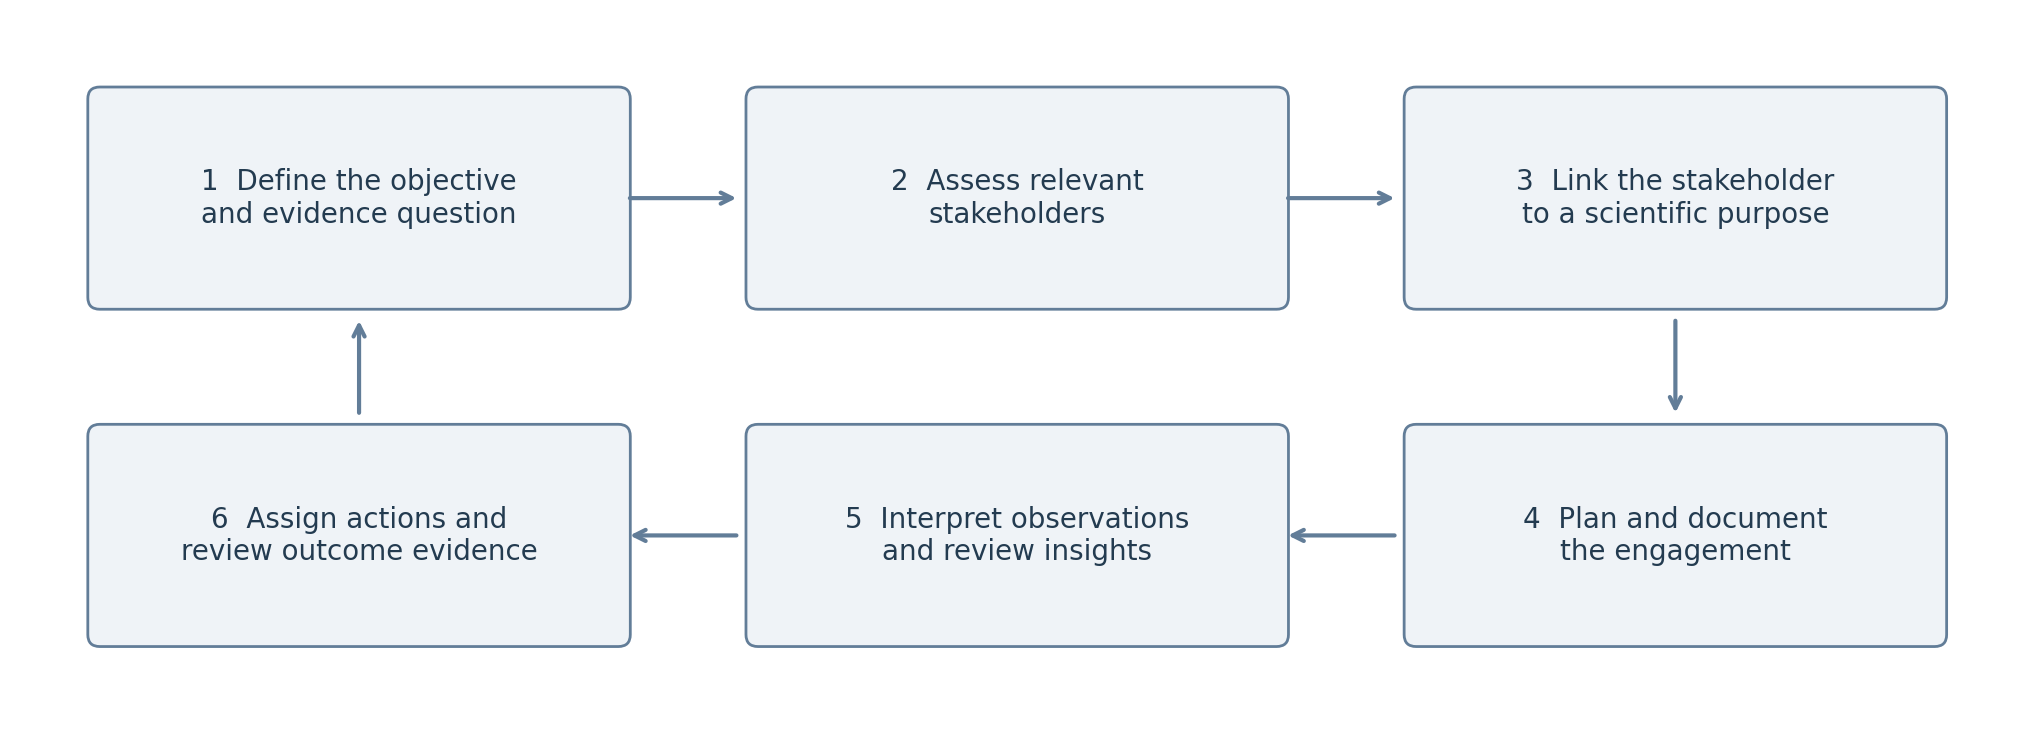
Figure 1. Proposed engagement planning cycle aligned with the workbook. Reviewing actions can reveal new or unresolved evidence questions. The diagram represents a workflow, not proven causation.
| Workbook tab | Planning role |
|---|---|
| Strategy Map | Define the medical objective, intended outcome measure, target, owner and review date. |
| Evidence Gaps | Record the question, available evidence, uncertainty and proposed approach. |
| Stakeholders | Maintain relevant expertise, scientific interests, assessment rationale and ownership. |
| Strategy Links | Connect stakeholder, strategy and gap IDs to an engagement objective and desired result. |
| Engagements | Plan the interaction and record the actual date, discussion and observed learning. |
| Insights | Separate observation, interpretation, evidence need and proposed action for review. |
| Actions | Assign an owner and due date; record completion and outcome evidence. |
In Strategy Links, create one row for each stakeholder–strategy–gap combination and avoid duplicates. Engagements reference the Link ID. Keep IDs consistent across the connected records; changing an ID without updating its references breaks the intended connection.
The workbook’s Ready status indicates that required information and relationships are present. It does not certify scientific accuracy, appropriate interpretation or approval for an external activity.
A fictional example from strategy to action
The following example follows records already present in the workbook’s fictional demonstration. It illustrates documentation and traceability. The people, institutions and findings are not real research evidence.
| Record | What the demonstration records |
|---|---|
| STR-001 | Objective: clarify evidence needs across specialist centres. Priority: understand pathway variation. |
| GAP-001 | Question: where does pathway variation occur? The demonstration records incomplete local pathway information. |
| KOL-001 | Fictional Dr Alex Morgan has scientific interests in pathway variation. |
| LNK-001 | Engagement objective: understand pathway differences. Desired result: document priority evidence questions. |
| ENG-001 | Scientific exchange completed on 10 September 2026. Recorded learning: two pathway uncertainties identified. |
| INS-001 | Observation: experts described pathway variation. Interpretation: variation may reveal unanswered evidence questions. |
| ACT-001 | Action: review and prioritise pathway evidence questions. Completed on 19 September 2026; two questions added to a draft evidence plan. |
Prepare questions that allow disagreement
For a discussion of pathway variation, useful prompts could include: “Which steps differ between settings?”, “What evidence supports that observation?” and “Where is the information incomplete?” These are proposed prompts, not a validated interview instrument. Avoid questions that assume the expected answer or suggest a conclusion before the evidence is reviewed.
Keep the observation separate from its meaning
“The expert described variation” records an observation. “Variation may indicate an evidence gap” is an interpretation that needs review. Neither statement establishes how common the variation is or whether it affects clinical outcomes. Record the source and context, and identify what additional evidence would be needed.
The MAPS white paper on medical insights describes an operational process for collecting, reviewing and sharing insights and linking them to action. It also emphasises a feedback connection between external stakeholder work and strategy. This is professional guidance, not validation of the demonstration findings. [2]
In this example, completing ACT-001 records an internal planning deliverable. It does not resolve GAP-001 automatically. The question can remain open until appropriate evidence and review support resolution.
Review progress without overstating impact
Use the dashboard to find work needing attention
Choose the reporting dates, country and therapy area in Configuration before interpreting the Dashboard. The selected period matters for completed engagements, coverage and actions closed. Open action counts include all dates, so they describe the current outstanding workload rather than only newly opened work in the period.
Tier 1 coverage is the number of distinct Tier 1 stakeholders with at least one valid completed engagement in the reporting period, divided by the Tier 1 stakeholders in the selected portfolio. Repeat meetings with one stakeholder do not add distinct coverage. A planned meeting does not count as completed coverage.
| Recorded measure | What it can establish | What it cannot establish alone |
|---|---|---|
| Completed engagement | An interaction has an actual date and documented learning. | Scientific quality or a change in clinical practice. |
| Stakeholder coverage | Distinct stakeholders have a valid completed engagement in the selected period. | Whether all relevant perspectives have been considered. |
| Insight recorded | An observation and interpretation have been documented. | That the interpretation is verified or representative. |
| Action completed | The record includes a completion date, outcome measure and result evidence. | Patient benefit or automatic resolution of an evidence gap. |
Review the substance behind the numbers
Ask whether the discussion answered the planned question, whether the interpretation is supported and whether an action is appropriate. Review unresolved scientific requests and overdue commitments. Where no follow up is justified, record that decision and its reason rather than creating an activity merely to increase a count.
A practical team review can examine a small sample of linked records as well as the totals. Check the fit between the objective and the stakeholder, the quality of the documented learning and whether completed actions produced the intended deliverables. This proposed review approach does not assign a universal performance target.
Keep execution within the appropriate process
A stakeholder link or a calendar entry does not approve a consultancy, study or advisory board. For example, EFPIA’s 2026 contracted services provisions require an identified legitimate need, relevant consultant selection criteria and a prior written contract. [3] This is an industry code example; requirements for an actual activity depend on its jurisdiction and applicable organisational procedures.
Route safety information and scientific requests through the relevant approved processes rather than leaving them solely in an insight or action log. Use nonidentifying summaries and organisation approved storage for real data. Define who reviews insights, who can agree actions and who confirms that an evidence question has been resolved.
Practical checklist and references
Before the engagement
• The medical objective, evidence question and reason for this stakeholder’s involvement are clear.
• The scientific topic, relevant sources, format and required reviews are prepared.
• The correct Link ID, owner and planned date are recorded.
After the engagement
• Record the actual date and observed learning before marking the engagement completed.
• Separate observation from interpretation and route the insight for appropriate review.
• Assign any justified action an owner, due date and intended outcome measure.
• Record completion evidence, then review whether the original gap remains unresolved.
References
1. Theron P, Britland M, Holder D, Ikeda Y, Rewers RF, Tiku A. Promoting Best Practices for Medical Science Liaisons Position Statement from the APPA, IFAPP, MAPS and MSLS. Therapeutic Innovation & Regulatory Science. 2021;55:1139–1144. doi:10.1007/s43441-021-00310-y.
Read the professional position statement
2. McLoughlin M, Jonkman M, Zivkov M. Building Medical Insights Capabilities in Medical Affairs Organizations. Medical Affairs Professional Society, Insights Focus Area Working Group. Undated white paper. Sections on definitions and objectives, process, inputs and outputs, and insight recipients.
3. European Federation of Pharmaceutical Industries and Associations. EFPIA Code of Practice. Final consolidated version 2026. Article 15, Section 15.02, page 23.
Online sources accessed 5 October 2026. References 1 and 2 provide professional recommendations; reference 3 is an industry code. They support the cited principles, not claims that this workbook or workflow has been clinically validated.
Companion resource and demonstration source
Stakeholder Strategy and Engagement System, version 3.1, 1 October 2026. The Strategy Map, Evidence Gaps, Stakeholders, Strategy Links, Engagements, Insights, Actions, Dashboard and Scoring Guide tabs are the source of the described fields, relationships, measures and fictional example. The article’s discussion prompts and practical review checklist are proposed professional approaches.
Stakeholder Strategy and Engagement System
Explore the workbook, its instructions and its fictional examples before adapting it to your team.
View the matching workbook